
AAPA Membership Invoice
Mail to:
Accounting
2318 Mill Road, Suite 1300
Alexandria, VA 22314
Fax: 703-684-1924
Please print, complete, and take to your employer for processing.
Name:
Address:
City, State, Zip:
AAPA ID:
Membership Type: Fellow
Please charge my:
☐ Visa ☐ MasterCard ☐ American Express ☐ Discover
☐ Check or money order, payable to AAPA (U.S. Currency Only)
Card Number:__________________________________________
Expiration Date:_______________ Security Code:_____________
Name On Card (Print name exactly as it appears on card):
________________________________________________
Signature: _______________________________________
Compare and see which membership fits you best!
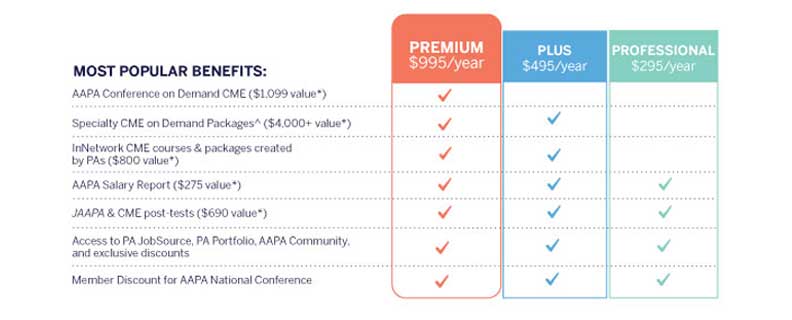
Fellow Membership Levels:
☐ $295 1 Year Professional Membership
☐ $495 1 Year Plus Membership
☐ $995 1 Year Premium Membership
Total Amount Enclosed:
By submitting payment, you are applying for membership in the American Academy of PAs and, if accepted, agree to support the Guidelines for Ethical Conduct for the PA Profession and adhere to AAPA’s rules and policies. For more information, please visit aapa.org/terms-of-use/terms-of-sale/
AAPA reserves the right to modify its membership tiers, benefits, programs or any aspect of the offering at any time.
*Values based on nonmember rates
^Adult Hospital Medicine Boot Camp on Demand, Executive Leadership on Demand, Family Medicine on Demand, Fluoroscopy Test Preparatory Course, Leadership and Advocacy Summit on Demand, Musculoskeletal Galaxy on Demand, Physician Assistants in Orthopaedic Surgery on Demand, Psych on Demand